
How to Know If Osteoarthritis Needs Knee Replacement?
Osteoarthritis can turn ordinary movements into daily negotiations. A short walk may bring swelling, grinding, or a deep ache behind the kneecap. Stairs, uneven ground, and putting on socks often reveal how much function has changed. Yet pain alone does not decide whether surgery is appropriate. Some people have severe X-ray changes but manageable symptoms. Others struggle with modest-looking scans.
This article explains how clinicians assess osteoarthritis and knee replacement as a possible treatment. It considers persistent pain, limited movement, sleep disruption, walking tolerance, and work or home demands. It also reviews treatments tried before surgery, including exercise therapy, weight management, medicines, injections, and walking aids. Evidence matters, but so does lived experience. An orthopedic specialist usually combines your history, physical examination, and weight-bearing X-rays. MRI is not always necessary. The decision should fit your health, goals, risks, and expectations.
A replacement may help when symptoms remain disabling despite appropriate nonsurgical care. It is not a guaranteed return to a pain-free, high-impact knee. Recovery requires time, strength, and practical support at home. Decisions are rarely perfectly clear. Even careful recommendations involve uncertainty. Online guidance cannot confirm surgical need. A qualified clinician should review your individual situation, especially if pain changes suddenly. Seek prompt medical advice if the knee locks, becomes severely swollen, or develops fever.
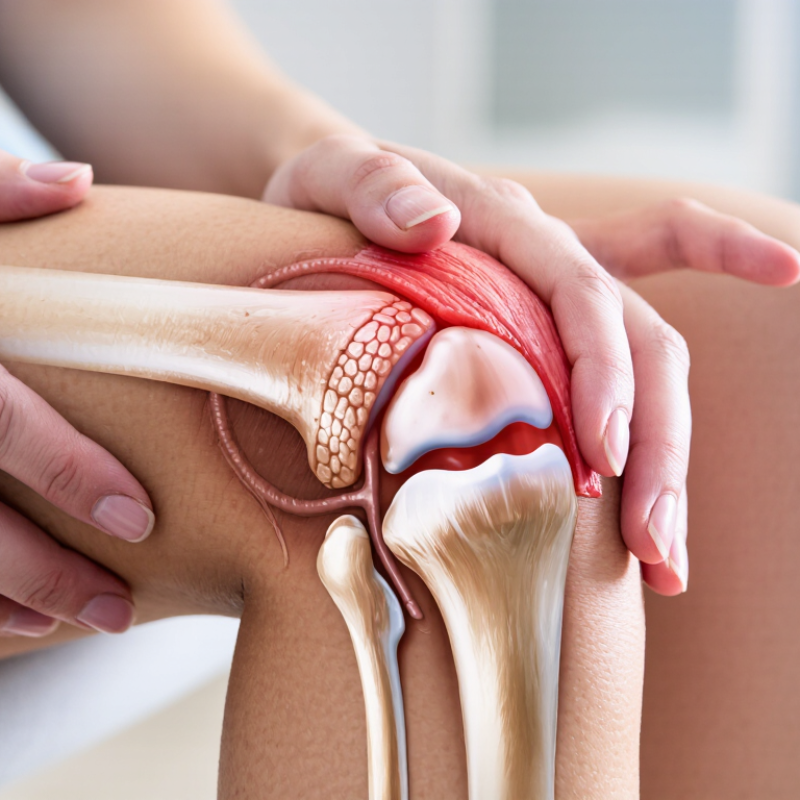
Understanding Osteoarthritis and Its Impact on the Knee
How to Know If Osteoarthritis Needs Knee Replacement?
Osteoarthritis develops when the knee’s protective cartilage gradually wears down. This change can expose bone surfaces and irritate nearby tissues. Pain may appear during stairs, walking, or standing after sitting. Stiffness often follows rest, especially in the morning. Swelling, grinding sounds, and reduced movement can also affect daily routines. Sleep may become difficult. Work can feel exhausting.
A knee replacement is usually considered when pain remains severe and limits ordinary activities. It may also be discussed when physical therapy, activity changes, medicines, or injections provide little lasting relief. The decision should not depend on an X-ray alone. Images can look severe while symptoms stay manageable. Sometimes, modest images accompany intense pain. That mismatch can feel confusing. A qualified clinician should compare your symptoms, examination findings, medical history, and imaging. Your goals matter too.
Tips: Track pain, swelling, walking distance, and sleep for two weeks. Notice which activities trigger symptoms. Bring this record to an appointment. Ask about strength, movement, non-surgical options, and realistic recovery needs. Do not rush because of one painful day. Equally, do not ignore pain that repeatedly limits bathing, driving, or climbing stairs. A second professional opinion may help when the recommendation feels unclear.
Recognizing Symptoms That May Indicate Advanced Joint Damage
How to Know If Osteoarthritis Needs Knee Replacement?
Recognizing Symptoms That May Indicate Advanced Joint Damage
Advanced knee osteoarthritis usually affects daily function, not only X-ray images. The World Health Organization reported that 528 million people lived with osteoarthritis in 2019. About 365 million cases involved the knee. Persistent pain during walking, climbing stairs, or standing may signal worsening disease. Pain that interrupts sleep deserves attention. So does swelling after short activity. Stiffness can make a knee feel locked each morning, although morning stiffness often lasts less than 30 minutes.
Other warning signs include reduced walking distance, repeated knee buckling, visible bowing, and difficulty rising from a chair. Imaging may show severe cartilage loss, narrowed joint space, or bone contact. However, an alarming X-ray does not automatically require replacement. The 2023 American College of Rheumatology and American Association of Hip and Knee Surgeons guideline supports surgery discussions when moderate-to-severe symptoms continue despite appropriate nonsurgical care. Decisions should include pain, function, medical risks, and personal goals. The imperfect part is important: pain scores and images do not always match.
Tips: Keep a seven-day symptom record. Note sleep disruption, walking distance, swelling, and medication effects. Ask whether physical therapy, weight management, walking aids, or pain treatment remain reasonable. Bring specific examples, such as “I stop after 100 meters,” rather than saying “my knee is bad.” A surgical opinion can clarify options, but it should not replace shared decision-making.
Evaluating When Nonsurgical Treatments Are No Longer Effective
How to Know If Osteoarthritis Needs Knee Replacement?
Knee replacement is usually considered when osteoarthritis continues to restrict daily life despite careful nonsurgical treatment. Persistent pain matters, but pain alone does not decide the timing. Doctors also assess walking distance, stair use, sleep disruption, swelling, and knee stability. A knee that hurts after a short grocery trip deserves attention.
Nonsurgical care may include physical therapy, weight management, activity changes, pain medicine, or injections. These options should have enough time to show whether they help. If pain returns quickly, movement remains limited, or treatment causes troubling side effects, the plan may no longer be effective. Keep a simple record for two weeks. Note pain levels, walking time, nighttime waking, and activities you avoid.
The decision still requires an examination and imaging. X-rays can show joint damage, yet they do not measure every person’s suffering. A severely damaged knee may remain tolerable, while moderate changes can feel disabling. That mismatch is real. Surgeons also review medical conditions, muscle strength, expectations, and recovery support before recommending surgery. A second opinion can be sensible when the recommendation feels rushed or unclear. Knee replacement is not a reward for enduring pain, and it is not always the immediate answer.
How to Know If Osteoarthritis Needs Knee Replacement? – Evaluating When Nonsurgical Treatments Are No Longer Effective
| Evaluation Dimension | What May Suggest Nonsurgical Care Is No Longer Sufficient | Typical Assessment or Evidence | What to Discuss With an Orthopedic Clinician |
|---|---|---|---|
| Persistent pain | Knee pain continues for several months, occurs most days, or interferes with sleep despite appropriate treatment. | Pain pattern, nighttime symptoms, pain score, and impact on daily activities. | Whether the pain is primarily caused by knee osteoarthritis and whether other causes should be ruled out. |
| Reduced daily function | Increasing difficulty walking, climbing stairs, standing, dressing, shopping, or completing household tasks. | Walking distance, use of a cane or walker, stair tolerance, and validated function questionnaires. | How much the limitation affects independence, work, exercise, and quality of life. |
| Failure of conservative treatment | A structured program of exercise, physical therapy, weight management when appropriate, medication, or injections provides inadequate or short-lived relief. | Treatment duration, adherence, degree and length of symptom relief, and side effects or contraindications. | Which treatments were tried, whether they were optimized, and whether alternatives remain reasonable. |
| Radiographic joint damage | Imaging shows advanced cartilage loss or joint-space narrowing that matches the location and severity of symptoms. | Weight-bearing knee X-rays may show joint-space loss, bone changes, osteophytes, or alignment changes. | Imaging should support the clinical findings; X-ray severity alone does not determine the need for surgery. |
| Knee alignment and instability | Progressive bowing or knock-knee alignment, recurrent giving way, or loss of confidence when walking. | Physical examination of alignment, ligament stability, range of motion, and gait. | Whether instability is caused by osteoarthritis and whether corrective or replacement surgery is appropriate. |
| Loss of range of motion | Increasing stiffness, inability to fully straighten the knee, or substantial difficulty bending it. | Measured flexion and extension, joint examination, and assessment for contracture. | Whether additional rehabilitation could help or whether structural changes are limiting motion. |
| Medication limitations | Pain medicines are ineffective, cannot be used safely, or cause unacceptable side effects because of other health conditions. | Review of kidney, stomach, heart, liver, blood-pressure, and bleeding risks, plus current medicines. | A personalized risk–benefit review rather than increasing medication without medical supervision. |
| Quality-of-life impact | The knee prevents valued activities, causes social withdrawal, or produces ongoing distress despite reasonable treatment efforts. | Patient goals, activity limitations, sleep quality, mood, and overall health status. | Expected benefits, recovery demands, rehabilitation plan, and realistic personal goals after surgery. |
| Health and surgical readiness | Symptoms are severe enough to consider surgery, but uncontrolled medical conditions or modifiable risks may increase complications. | Assessment of general health, blood sugar control, weight-related risks, smoking, infection risk, and home support. | How to optimize health before surgery and whether medical clearance is needed. |
| Urgent symptoms | A hot, red, acutely swollen knee; fever; sudden inability to bear weight; severe calf swelling; or sudden chest pain or breathlessness. | These symptoms may indicate infection, fracture, blood clot, or another condition rather than routine osteoarthritis. | Seek urgent medical evaluation. Do not wait for a routine knee-replacement consultation. |
Knee replacement is generally considered when pain and functional limitations remain substantial despite appropriately supervised nonsurgical treatment, and examination and imaging support advanced joint disease. The decision should be individualized with a qualified healthcare professional.
Assessing Medical Criteria for Knee Replacement Surgery
How to Know If Osteoarthritis Needs Knee Replacement?
Knee replacement is considered when osteoarthritis causes persistent pain and limits daily function. Walking to the mailbox may become difficult. Stairs can feel unsafe. Some people struggle to sleep because of aching or stiffness. These changes matter more than an X-ray alone.
An orthopedic evaluation usually includes your medical history, physical examination, and weight-bearing knee images. The clinician checks alignment, joint movement, swelling, muscle strength, and tenderness. Imaging may show severe cartilage loss or bone contact. However, severe-looking images do not always match severe symptoms. That mismatch deserves careful discussion.
Doctors often recommend trying non-surgical care first, unless disability is extreme. Options may include targeted exercise, weight management, physical therapy, walking aids, or appropriate medication. Injections can help some patients, but benefits vary. Surgery becomes more reasonable when pain continues despite well-managed treatment and daily activities remain restricted. Overall health also matters, including diabetes control, heart conditions, smoking, and the ability to complete rehabilitation. A replacement is major surgery. It has risks, such as infection, blood clots, stiffness, or continuing pain. Recovery may take months, not weeks. I have found that patients sometimes focus only on the scan and underestimate rehabilitation demands. That is a common mistake. A second professional opinion can clarify uncertain cases. The decision should reflect symptoms, examination findings, medical risks, and personal goals, not a single test.
Preparing for Consultation, Surgery, and Recovery Planning
How to Know If Osteoarthritis Needs Knee Replacement?
Preparing for a knee replacement consultation starts with honest daily details. Record pain levels, swelling, stiffness, and walking distance for one week. Note whether stairs, sleep, or dressing have become difficult. An orthopedic specialist will review your medical history, examine knee movement, and study imaging. However, an X-ray alone does not decide surgery. The decision usually considers persistent symptoms, reduced function, and limited improvement from treatments such as exercise, weight management, medication, or injections.
Bring a current medication list and questions about implant options, anesthesia, risks, and expected movement. Share conditions that may affect healing, including diabetes, heart disease, or previous infections. Ask how long you may need assistance at home. Recovery planning should begin before surgery. Clear loose rugs, prepare a sleeping area, and arrange transportation. A physiotherapist can explain early exercises, walking aids, and realistic milestones. Full recovery varies, and progress is rarely perfectly steady.
Tips: Ask someone to join the consultation and take notes. Request written instructions about wound care and warning signs. Practice using a walker if recommended. Plan simple meals and place essentials at waist height. Do not hide fears or doubts; they may reveal important questions. A common mistake is planning only for the operation, not the quiet, tiring weeks afterward. Your surgeon and rehabilitation team should tailor advice to your health, home, and goals.
Related Posts
-
Why Is Knee Replacement Needed for Arthritis?
-

How to Know If Osteoarthritis Needs Knee Replacement?
-
What Is the Best Knee Surgery for Osteoarthritis?
-

Top 10 Questions About Arthritis and Knee Replacement
-
Why Is Osteoarthritis Knee Surgery Needed?
-
How to Choose Knee Surgery Options for Osteoarthritis?
DISCOVER THE POTENTIAL OF INNOVATIVE PROSTHETICS
From minor to severe injuries, our team develops advanced devices designed to support recovery and promote overall wellness.
