
What Is the Best Knee Surgery for Osteoarthritis?
Choosing the best osteoarthritis knee surgery is rarely a simple matter of naming one procedure. Pain, stiffness, age, activity level, joint damage, and overall health all influence the decision. A knee that hurts after a short walk may need a different solution from one that remains painful while resting.
Many people first consider medication, physical therapy, weight management, injections, or walking aids. These options may reduce symptoms and improve movement, especially when surgery is not yet necessary. However, advanced cartilage loss can continue affecting daily life. Climbing stairs, standing from a low chair, or sleeping through the night may become difficult.
When conservative care no longer provides enough relief, an orthopedic specialist may discuss osteoarthritis knee surgery. Possible procedures include partial knee replacement, total knee replacement, and, in selected cases, osteotomy. Arthroscopy usually has limited value for typical age-related osteoarthritis, unless another problem is present.
There is no universally “best” operation. The most appropriate choice depends on X-rays, physical examination, pain patterns, ligament stability, and personal goals. A surgeon’s experience matters, but so does honest discussion about recovery, risks, implant lifespan, and realistic outcomes. Most patients want to walk comfortably again, not simply receive a technically successful operation.
The decision is not always clear. Even careful evaluation has limits, and recovery can be slower than expected. A second opinion may help when recommendations differ. This guide explains the main surgical options, who may benefit, and what questions to ask before making a well-informed decision.
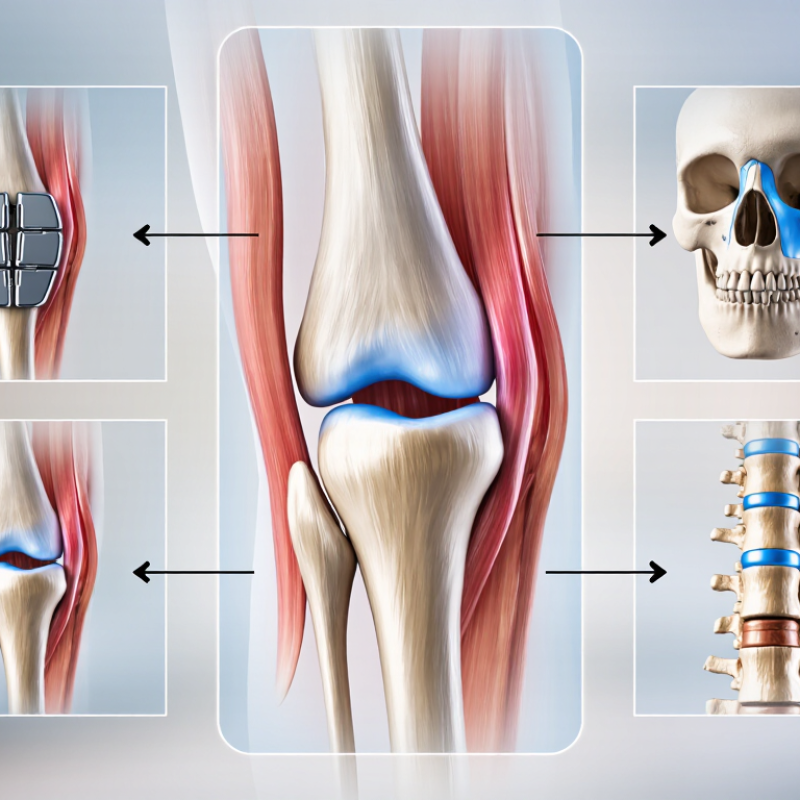
Table of Contents
[Hide]
Understanding Knee Osteoarthritis and When Surgery Is Needed
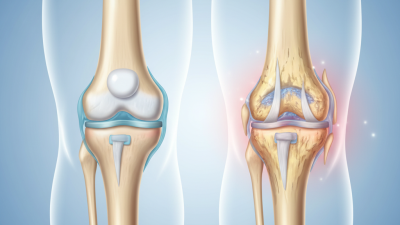
Knee osteoarthritis develops as cartilage and other joint tissues change over time. The knee may feel stiff after sitting, ache on stairs, or swell after a long walk. Some people notice grinding or reduced motion. These symptoms can interfere with sleep, work, and ordinary tasks, but an X-ray alone does not explain how much pain someone feels.
Treatment usually begins without surgery. Activity adjustments, strengthening exercises, physical therapy, and appropriate pain medicines may help maintain movement and reduce discomfort. A clinician can review symptoms, examine the knee, and consider imaging alongside a person’s health and goals. Surgery may be discussed when pain remains substantial despite reasonable nonsurgical care, or when walking and daily activities become persistently difficult. There is no single timetable.
The best decision is personal. Age, overall health, knee alignment, and the extent of joint damage can all matter. Total knee replacement may be considered when damage affects much of the joint; partial replacement may suit some people with disease limited to one area. Neither choice guarantees a pain-free knee or an effortless recovery. Discuss likely benefits, risks, rehabilitation, and alternatives with an orthopedic professional. It is worth asking what improvement is realistic—and what limitations might remain.
What Is the Best Knee Surgery for Osteoarthritis?
There is no single best operation for everyone. The appropriate procedure depends on which parts of the knee are affected, alignment, symptoms, overall health, activity goals, and whether nonsurgical care has provided enough relief.
| Procedure or care option | When it may be considered | What it does | Potential benefits | Important limitations |
|---|---|---|---|---|
| Total knee replacement (total knee arthroplasty) |
Advanced osteoarthritis affecting multiple areas of the knee, with substantial pain or disability despite appropriate nonsurgical treatment. | Damaged joint surfaces are replaced with artificial components. | Often reduces pain and improves everyday function for people with severe knee arthritis. | Major surgery with risks such as infection, blood clots, stiffness, and persistent pain. Recovery and rehabilitation take time; the artificial joint may eventually wear or need revision. |
| Partial knee replacement (unicompartmental knee arthroplasty) |
Arthritis is limited to one compartment of the knee, with suitable ligaments, alignment, and remaining joint surfaces. | Replaces the damaged compartment while preserving more of the natural knee than a total replacement. | May preserve more natural knee structures and can involve a smaller operation for appropriately selected patients. | Not suitable when arthritis is widespread or other selection criteria are not met. Arthritis can progress in other compartments, and further surgery may be needed. |
| High tibial osteotomy | Some younger or more active people with arthritis mainly on one side of the knee and a correctable alignment problem. | Reshapes the upper shinbone to shift load away from the more damaged compartment. | Can preserve the natural knee joint and may delay the need for knee replacement in selected cases. | Requires bone healing and rehabilitation. It may not be appropriate for widespread arthritis, and pain relief is not guaranteed. |
| Arthroscopy | May be used for a separate problem, such as a loose body causing true mechanical locking, when clinically appropriate. | Uses a small camera and instruments to inspect or treat specific structures inside the joint. | Can address certain mechanical problems that coexist with arthritis. | Arthroscopy generally does not improve pain from knee osteoarthritis itself and is not a routine arthritis treatment. |
| Nonsurgical treatment | Usually considered before surgery and may continue at any stage, depending on symptoms and individual circumstances. | May include exercise or physical therapy, weight management when appropriate, walking aids, and clinician-guided pain relief. | Can reduce symptoms and improve function without the risks and recovery demands of an operation. | It does not replace the joint; benefits vary, and some people with advanced disease continue to have substantial symptoms. |
How to decide: A clinician can review symptoms, examination findings, imaging, medical history, and personal goals to discuss suitable options and risks. Surgery is generally considered when knee symptoms substantially affect quality of life and nonsurgical measures have not provided adequate relief. This table is general educational information, not a diagnosis or an individualized treatment recommendation.
Related Posts
-
Why Is Osteoarthritis Knee Surgery Needed?
-
How to Choose Knee Replacement for Osteoarthritis?
-

Top Ways to Manage Arthritis in Your Knee Effectively?
-
Top 10 Facts About Knee Replacement Due to Osteoarthritis in China
-

2026 Best Ways to Prevent Osteoarthritis for a Healthier Future?
-
What is Osteo Arthrosis and How Does It Affect Joint Health?
DISCOVER THE POTENTIAL OF INNOVATIVE PROSTHETICS
From minor to severe injuries, our team develops advanced devices designed to support recovery and promote overall wellness.
Contact Us